Sarah, Malakai's mother, had 3 home births prior to discovering that she was a hemophilia carrier. This is the story of their birth planning after that discovery.
I didn't realize how emotional it would be to revisit my pregnancy with Malakai. I've shared my birth story with so many, but his story begins a few months before he was created. . .
One month before Elijah was a year old, I got the news that I was indeed a carrier of severe hemophilia A. (For those who aren't as familiar with hemophilia: It is possible that a hemophiliac is the result of a spontaneous mutation, and did not inherit the gene from a parent.) That was November 2008. In March 2009, we found out that we were expecting #4. Within the next month or two after that, my husband learned that he was losing a huge part of his job that would make it impossible for us to stay in CA. This was a very personal thing, and not just a business downsize. Also, Elijah was one week from his port surgery. I was under extreme stress, and had to choose where my energy would be spent. That was not a hard choice. I had to take care of my family. My husband needed a lot of support, I was growing a baby that needed me, and I was gearing up to hand off my older baby to surgeons. There was no room for anything else. But, still, it didn't make all the other pressure go away. On top of all that, I had to start planning my upcoming birth. We got an ultrasond to determine the sex of the baby. It was a boy! I started doing extensive research on hemophilia and childbirth, and was not satisfied with what I found. I'll get into that in another post.
Several facts were in the mix: 1. Our baby had a 50% chance of having severe hemophilia. 2. I had to plan my birth with wisdom in the new knowledge that I could pass on this gene. 3. I could not base my decision on the success of Elijah's birth, although that did play a part in the decision. All hemophiliacs are not the same, and have different bleeding patterns. 4. Until my third trimester, I did not have any idea where we would be for the birth. 5. We needed to have his blood tested right after his birth. 6. My son's hemotologist recommended that I schedule a c-section. Then, when she could see that I was not welcoming that idea, she recommended a plan B: Have my birth as natural as possible in a hospital where they can do an emergency c-section if needed.
Near the end of my second trimester, my husband was offered a job in NY. He accepted the position, and we had to pack up our house in a week. We decided to drive. After all, when would we ever get the oppurtunity to drive from CA to NY again?! So, Matt drove the big truck, and I drove the van. Yeah, it was pretty crazy! It was fun though. We made lots of memories. I met with the ONLY licensed midwife in the Buffalo area a couple weeks later. We were planning a homebirth, hoping the local hospital would support running the labs for us (Matt would take the blood to the hospital immediately). In some cases, this does work, however, in ours, it did not. Our new ped. hemotologist tried to work out the labs for us, and even an on call emergency transport. However, the hospital would not support this plan. Our midwife, who we loved, could not help us with a homebirth. She was under fire from the hospital, and could only offer to help us with a hospital birth. I was devistated. We met with another midwife, but we couldn't work out the labs. I met with the nurse manager at the hospital. I told her that I wanted a waterbirth. She told me that they did not offer waterbirth, and the room was so small that it just wouldn't work. I was determined to have the most relaxed non-traumatic birth possible even if that meant having my baby at home and compromising the immediate lab work. I was trying to avoid causing my baby a bleed. I would keep him safe!! I met with the perinataltologist who asked me about my birth history and what I wanted for this birth. When she heard my reasoning and that my only concern was the safety of my baby, she told me that I should get exact measurements of the birth pool, and get them to the nurse manager. I did, but the NM said there was simply no room. I asked her if we could make room for the pool by moving the bed to the hallway. She said I shouldn't hope for this to be approved, but she would speak to "the powers that be", and get back to me. I again shared my heart for my baby's safety with her. The next morning, I wept tears of joy when the NM called me and told me to order the pool!!

Showing posts with label safety. Show all posts
Showing posts with label safety. Show all posts
Thursday, August 25, 2011


Monday, August 15, 2011
Confession
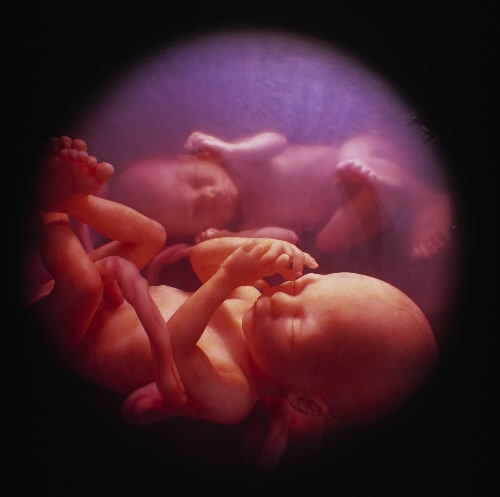
Foremost on my mind: TWINS
I seem to be carrying larger than usual with this pregnancy, enough that I myself have wondered if I might be carrying multiples. It's not logical. There's no family history of multiples that I'm aware of, and I haven't undergone fertility treatments or done anything else I'm aware of that could increase my chances of having twins. But the thought is there, and it keeps coming back.
I've scheduled an ultrasound in a few weeks. I really want to confirm or rule out this thought. I don't think I'd be surprised to find I'm further along than I thought (despite my dates) or that there is more than one baby in there, simply because of the size of my belly.
Is this crazy? Maybe. I never claimed to be sane, especially during pregnancy. In fact, I believe pregnancy gives me the right to be a crazy lady. I can't seem to control it anyway.
What if I'm carrying twins?
My birth plans wouldn't change. I'd still plan a home birth. In fact, my midwife has already promised me that she'd be hands off even if I had twins. Her words, not mine. She's a very intuitive woman. Does she have some kind of inkling she hasn't told me about yet? Hmmm. I may have to ask her at some point.
What would change? Mainly, we'd need a bigger vehicle and we'd have to move. It's in our lease agreement that we can't live here with more than 6 children, so we'd have to start looking for a new place to live. We just bought a van a few months ago that has 8 seats. Yeah, we'd have to sell that and start looking for something bigger. I might end up with one of those full size vans that seats 12 or 15. Think of the space!
Am I scared? Not particularly. I'm grateful for whatever we'll be given, even if that means two babies for the price of one. I have no clue how I'd handle the logistics of 7 children under the age of 12, the youngest 2 being twins. Yeah, things would definitely be interesting, even more so than they are now, in our house. But we can handle whatever we get, whether we think we can or not. I'm stronger and more capable than I give myself credit for.
So there it is. My pregnancy confession. Now, how sheepish would I feel if we have the ultrasound and find that there's only one baby in there? Oh well. At least we could keep our van and our home, and I already know I can handle one baby at a time.
Friday, April 8, 2011
Giving Birth Unassisted: an Option for Me
This is an article I wrote for the Pampers website, but it was rejected because unassisted birth is not considered safe by the medical community. I was encouraged by my readers to share it here instead. Thank you for reading and for your continued support. I hope you enjoy it.
(Also published on The Birthing Site)
(Also published on The Birthing Site)

Giving Birth Unassisted: An Option for Me
Before I got pregnant I thought birth was inherently dangerous and all women needed to be in the hospital to give birth. I'd never heard of women giving birth unassisted, and even the idea scared me. Through personal experiences and time I've come to reconsider my previous ideas, and I now embrace the idea as an option for expectant women.
As I've come to understand it, the concept of giving birth unassisted is when an expectant mother plans to birth without a professional care provider present, but it's sometimes used to describe a situation when a woman's labor goes so fast that she doesn't get the care she planned for. I've heard stories of women who unexpectedly gave birth at home, in the car, or somewhere else, often on the way to the hospital. A friend of mine recently had an unexpected unassisted birth when her midwife didn't arrive in time for the home birth. My friend had her husband's support and gave birth to a healthy baby.
I have a few friends who planned to give birth unassisted for various reasons. Some of my friends requested the presence and support of family members or friends, and some of them chose only to be supported by their husbands. Their reasons are intensely personal, and none of them made the decision lightly. My friends felt confident in being able to give birth without professional support, but they also took precautions by educating themselves and having supplies available, as well as being close to emergency services. I've read some amazing birth stories of birth transfers under emergency situations which ended well even when quick action was needed.
The idea of giving birth unassisted doesn't scare me like it used to. One thing I've learned through my own birth experiences is that I can give birth with very little support or intervention. When I gave birth without medication in the hospital there was very little the staff did for me. They mostly watched to ensure that all was well, and I did the work myself. These experiences helped me plan a home birth with my fifth child. I knew I could give birth without the machines and other things at the hospital because I'd done it even while in the hospital. I hired a midwife to support me, and I'm glad I did. I had an unexpected breech baby and my midwife helped me through it to have a vaginal breech birth.
Because of my growing comfort level with the process of giving birth, I'm personally open to the option of giving birth unassisted in the future. My friends who gave birth unassisted had prenatal care and prepared by doing research and learning what to have ready and what to watch for. They have wonderful stories to tell about the births of their babies.
Friday, April 1, 2011
VBAC Video: This Woman's Work
"... a three year journey that took this couple from their unexpected hospital cesarean birth to birthing their second baby at home in water - condensed into a mere 6-minute video. You, the viewer, become a witness to their very heartfelt, personal sacrifice and transformation."
I first saw this on The Beginning of Motherhood
Monday, February 21, 2011
Should You Get Induced? - Part 2
This is the second video in a series about induction. Click here to watch the first video.
Monday, October 4, 2010
Midwife/Home Birth Animation
Here's another fun poke at stereotypes regarding midwives and home birth...
Monday, July 26, 2010
The Home Birth Controversy
 Depending on who you talk to, home birth is either the best thing you can do for the safety of your baby, or the worst. Who are we to believe?
Home Birth has been in the news a lot lately. Just one day after legislation was passed in New York allowing midwives to practice independently of physicians, a meta-analysis of home birth studies was publicized by the American Journal of Obstetrics and Gynecology, slamming home birth and claiming that home birth "triples risk of infant death". The Unnecesarean and the Midwife Next Door both chimed in, among others, refuting the meta-analysis and exposing it's faults.
One thing I like to remember is to recognize the source. If a study or analysis is being publicized by AJOG, which is the journal of the American Congress of Obstetrics and Gynecology, then it's going to favor the positions which ACOG has taken on issues. ACOG is a lobbying group, which serves to protect the interests of physicians and hospitals. Groups like the American Medical Association and ACOG have taken strong positions against home birth for a reason. They have financial interest in hospitals and doctors. They lose money when women choose to birth at home. If you read the scathing reviews on the recent meta-analysis you'll see that the analysis contradicts itself. The studies used in the analysis don't support the findings, and the analysis itself contains contradictory information.
You must look closely. Don't take things at first glance, and don't put stock in a catchy headline. Read and do your research. You may find, as I have, that modern obstetrics is not based on evidence. It's based on what's profitable and convenient for the system that's in place.
Do your homework. Read books, like "Get Me Out; A History of Childbirth from the Garden of Eden to the Sperm Bank", "Pushed" by Jennifer Block, "The Thinking Woman's Guide to a Better Birth" by Henci Goer. Watch "The Business of Being Born" by Ricki Lake and Abby Epstein. Read any of the books written by Ina May Gaskin.
Jennifer Block wrote a really good piece: The Birth Wars: Who's really winning the home birth debate?
We see so much about hospital birth because 99% of babies are born in the hospital in the US. If you want to learn about the safety of home birth, you have to look for it and find the sources. Here are some you can start with:
- The Home Birth Advantage: The Physical and Emotional Benefits of Birthing at Home
- Midwifery Today: The Home Birth Choice
Ultimately, it is YOU who must decide what's best for you. After you've done your research and educated yourself, search yourself and see what feels best in your heart. I believe that intuition can guide us to make the best choices. Avoid making a choice based on fear. This is where the education comes into play. When you're fully informed, you have no need to fear. If you feel peace about home birth, then you know it's a good choice for you. If you still have doubts or fears about it, keep researching and reconsidering until you come to a decision you feel comfortable with.
Busca on Birth Faith posted a really interesting piece about the irrelevance of the place of birth: The irrelevance of home vs hospital. She states that the place of birth is less important than the support a woman receives through labor and birth. I personally feel that both are equally important, but you must come to your own opinion.
You may decide that home birth isn't for you. You want or need to be in the hospital, but you want it to be a beautiful experience. There is a book called Homebirth in the Hospital, which can help you plan and prepare for a beautiful hospital birth.
Wednesday, June 16, 2010
Rising Maternal Mortality Rate Causes Alarm, Calls For Action

"Each day in the U.S., two women die of problems related to pregnancy or childbirth. The numbers have been rising, for reasons that are not entirely clear."
"Nationally, the rate, defined as deaths from obstetrical causes within one year of giving birth, rose from 7.6 per 100,000 to 13.3 per 100,000." (emphasis mine)
This excellent article discusses the rising problem of maternal mortality, and some of the possible causes including: the rising c-section rate, increasing use of medical labor induction, and the changing profile of American mothers (more older women having babies).
The problem is baffling for experts, because high death rates are common in poor countries where women don't have access to adequate prenatal care. The United States, however, spends the most money on health care, yet has one of the highest rates of maternal mortality.
"Though the U.S. spends more per birth than any other nation, maternal mortality is higher here than in 40 other industrialized countries, including Croatia, Hungary and Macedonia, and is double that of Canada and much of Western Europe."
"That the United States is backsliding in this most basic of healthcare measures has triggered attention and alarm in medical circles. In January, the Joint Commission, an independent organization that accredits and certifies healthcare organizations and programs, issued a "sentinel event alert" warning of the rising maternal mortality rates.
"In March, the human rights organization Amnesty International released its own report, 'Deadly Delivery,' calling for sweeping changes in maternal healthcare in the U.S."
"The California Department of Public Health has commissioned a statewide review of medical charts in maternal death cases to identify reasons for the rise and seek ways to improve."
"'Mothers shouldn't die in childbirth,' said Dr. Elliott Main, chief of obstetrics at Sutter Health and director of the ongoing California review. The trend, he said, may signal a much larger problem with U.S. maternal healthcare."
Here are some more articles on the subject:
Wednesday, May 26, 2010
VBAC Articles

Friday, May 7, 2010
Avoiding The First C-Section

In honor of Cesarean Awareness Month, featured in the Courtroom Mama blog, I am continuing the topic of avoiding the first c-section. Why is it so important to avoid the first one?
- It’s major abdominal surgery, and carries increased risks for mother and baby
- It often puts the mother in the position of having repeat c-sections, because she cannot find support for vaginal delivery after a cesarean
- It increases the risk of abnormal implantation of the placenta, which can lead to hemorrhaging or need for hysterectomy
- It increases the risk of unexplained stillbirth in a subsequent child.
No one will argue that c-sections can be lifesaving under certain circumstances. Placental separation, placenta previa, cord prolapse, and certain abnormal presentations of the baby might cause injury or death to mother and child if it were not for the ability to deliver a baby by cesarean. I am thankful we have the ability to perform this surgery in a very safe manner. However, the majority of c-sections are not done for emergent, life-saving reasons. It’s those c-sections I want to focus on preventing.
Since most women having a primary (first-time) c-section are also having their first baby, I have five simple precautions that have been invaluable in my practice in helping women to avoid a c-section. I am writing from the perspective of hospital birth, knowing that the majority of women will not choose home birth, although I believe this is the number one way to avoid a c-section:
1. Stay at home in labor as long as possible, and consider giving birth at home. Why?
- Consider an animal in labor. If you’ve ever observed a cat or dog preparing to give birth, you may have noticed that they seek solitude. If they are disturbed during labor, they ahve a natural “fight or flight” reflex that slows or halts labor, allowing them to move to a safer location. While we as human women can intellectually understand the reasons for moving to another location (the hospital) to give birth, our bodies may still respond with a slowing of the labor process.
- It is understood that pain relieving medications can have a slowing effect on the process of labor. Epidurals are associated with a higher rate of vacuum, forceps and cesarean births in some studies. Yet it is difficult for a woman in hard labor to resist the offering of total relief of her pain. When you are at home, you know the pain medication is not available, and so the mind does not focus on it. It is easier to work with the contractions when you aren’t constantly thinking of the epidural available to you in only minutes.
- Staying home in the earlier stages of labor helps you to avoid the urge that hospital staff will feel to “speed things along” if your first part of labor takes many hours. It is common for dilation from zero to four or five centimeters to take many hours, and sometimes more than one day. If you are in the hospital and you are not yet dilated to four centimeters and having contractions three or four minutes apart, you are not in active labor. This part of labor is best spent at home.
2. Hire a doula if you can possibly afford it. If not, seek out an older woman who has had several children naturally herself, or has been present at several natural births, to be with you at home until you decide to go to the hospital.
- A woman who is familiar with the process of a normal birth will be invaluable to you in helping you know when it is time to got to the hospital. She can reassure you that what you are feeling is normal, that you can do it, and that you are stronger than you think.
- Many women are afraid to stay home in labor. A doula or experienced woman will be aware of the normal process of labor and be able to help you feel calm about laboring at home.
3. Find a practitioner who does not put arbitrary time limits on how long you can be in labor. If you are feeling strong, the baby is doing well, and you want to keep going, there should be nor reason to rush to a c-section simply because the labor is taking longer than average.
4. Carry on your usual activities as long as possible. Far too many first-timers make the mistake of doing everything they can to speed labor along. All too often, their efforts succeed at nothing but making them miserable and exhausted. Allow labor to unfold in its own time. Ignore the contractions until you are physically incapable of doing anything else during a contraction as well as in between contractions. This is where many women take their labor too seriously. They think because they have to breathe with a contraction, they are in hard labor. The actions of the mother between contractions are more indicative of the stage of labor. During the latter stages of dilation, the woman is usually quiet, tired, and may even fall asleep between contractions. She does not feel like talking much, or doing anything but resting before the next contraction. If your labor starts in the day, do what you normally would have been doing if you’d not started labor. If your labor starts at night, stay in bed and try to sleep, at least between contractions. If you cannot sleep, at least rest until your normal getting-up time.
5. Stay off the fetal monitor! The American Congress of Obstetricians and Gynecologists has published guidelines for intermittent auscultation of the baby, stating that it is just as safe for low-risk pregnancies as continual monitoring. It has the added benefit of having a lower c-section rate. This suggests that many c-sections are done for “fetal distress” seen on the monitor tracing, when the baby is actually fine. Once you allow someone to connect you to the continual monitor, you most likely won’t be off of it for the rest of your labor. What is intermittent auscultation? It is not being connected tot he monitor for 20 minutes out of every hour, as many hospitals’ protocols require. Rather, it is listening to the baby’s heart rate with a hand-held doppler before, during, and after a couple of contractions every 15-30 minutes during the first stage of labor. A skilled practitioner can determine if the criteria indicating fetal well-being are present, even with a hand-held doppler.
There you have it–my top five precautions to avoid the first c-section. I’d love to hear your ideas for other ways to avoid an unnecessary cesarean.
Wednesday, April 14, 2010
New Moms at Risk - Maternal Death Rates Increasing
Maternal death rates are on the rise, and it's getting some well-deserved attention. In our world of modern obstetrics with advanced technology, one would think that fewer mothers would be dying during or after childbirth, but the opposite is true.
That article caught my attention. It was a bit shocking to see the statistics and realize the real impact this is having on real mothers and their families.
According to the statistics from California, the increase in mothers dying is the result of the overuse of interventions such as c-sections and medical induction.
C-section rates are higher than ever. The US has an overall c-section rate of about 33%, with hospitals in some areas boasting rates close to 50%. That means that in the United States, 1 out of every 3 babies is born by c-section. The World Health Organization recommends a safe c-section rate for developed countries (like the United States) is 10-15%. They also state that when the c-section rate is more than 15% the risks outweigh the benefits and more mothers and babies are at risk for complications. Complications that are completely avoidable.
Amnesty International is concerned and advocating for changes in maternal health care:
"According to Amnesty, which gathered data from many sources, including the Centers for Disease Control and Prevention, approximately half of the pregnancy-related deaths in the U.S. are preventable, the result of systemic failures, including barriers to accessing care; inadequate, neglectful or discriminatory care; and overuse of risky interventions like inducing labor and delivering via cesarean section. 'Women are not dying from complex, mysterious causes that we don't know how to treat,' says Strauss. 'Women are dying because it's a fragmented system, and they are not getting the comprehensive services that they need.'"
"In the U.S., we spend more than any country on health care, yet American women are at greater risk of dying from pregnancy-related causes than in 40 other countries."
ABC has reported about the statistics in California and brought some much-needed attention to this problem. One thing they recommend in this video: avoid unnecessary interventions during pregnancy and birth. This means avoiding induction, scheduled c-sections and other interventions unless they are medically necessary.
What do you think? What else can women do to protect themselves from the dangers of overaggressive obstetrics?
Monday, November 2, 2009
Advice regarding breastfeeding for mothers with possible H1N1 infection
 "Advice regarding breastfeeding for mothers with possible H1N1 infection
Ruth A. Lawrence, M.D., FAAP and John S. Bradley, M.D., FAAP
As published in AAP News - Official Magazine of the American Academy of Pediatrics
"Neonates and infants younger than 6 months of age are at risk for complications from seasonal influenza and presumably 2009 H1N1 influenza (swine flu), although the morbidity and mortality from this new virus have not yet been described.
"While the advantages of breastfeeding are well-known, this close interaction of mother and newborn also can facilitate transmission of influenza virus. The benefits and the risks of close contact must be considered carefully.
"To protect the infant from possible serious infection while allowing essential and encouraged mother-infant bonding to occur, a compromise is required until more data are available. The following precautions are suggested to minimize the risk of infection to the infant, particularly while still in the hospital and while the mother is symptomatic with fever and coryza:
"Pay careful attention to handwashing prior to any contact. Prior to breastfeeding, wash the breast with mild soap and water; rinse well The mother should wear a surgical mask to prevent nasal secretions and the spontaneous cough or sneeze from inoculating the infant. Use clean blankets and burp cloths for each contact. Monitor the maternal-infant interaction on perinatal floors for compliance with the above precautions. These precautions are designed to minimize the risk of transmission until mother’s immune response to H1N1 influenza is established, and increased, specific immune protection may be provided by breast milk. Note that influenza virus does not pass through breast milk.
"Although the most effective way to prevent influenza transmission is complete separation from her infant when a mother is receiving antiviral treatment, separation may create more long-term problems in breastfeeding success and mother-infant bonding than any potential benefit achieved from avoiding infection in the newborn infant.
"For any mother with H1N1 influenza infection who presents in labor to a health care institution, testing and empirically starting therapy for influenza with an antiviral is suggested. Oseltamivir (Tamiflu) or zanamivir (Relenza) will hasten resolution of symptoms and infectivity, particularly if treatment is started within 48 hours of onset of illness. Neonatal exposure to oseltamivir (Tamiflu) excreted in breast milk is extremely low.
"Immediately following delivery, the precautions listed above should be instituted as the newborn infant is first placed into mother’s arms. These precautions should be followed until mother’s illness is resolved, i.e., no fever, as measured without antipyretics, for 24 hours.
"While no data exist to support these suggestions, it is believed that these represent an appropriate balance between the benefits of mother-infant interaction and the risks of serious neonatal infection. Institutions may wish to modify of these suggestions to address their needs and medical practices.
"Dr. Lawrence is chair of the AAP Section on Breastfeeding executive committee. Dr. Bradley is a member of the AAP Committee on Infectious Diseases."
Thursday, February 5, 2009
Study: Elective C-section babies born before 39th week face risks
You learn something new every day. At least, I do, and I like it that way.
I just learned today that babies born via Cesarean Section are more likely to have respiratory problems compared to babies born vaginally. A recent study tracked more than 24,000 women who had repeat c-sections performed at 37 weeks or later. Of those women, 13,258 had elective c-sections, meaning it was simply by choice with no medical basis for the surgery. Some of the main points of the study are:
I just learned today that babies born via Cesarean Section are more likely to have respiratory problems compared to babies born vaginally. A recent study tracked more than 24,000 women who had repeat c-sections performed at 37 weeks or later. Of those women, 13,258 had elective c-sections, meaning it was simply by choice with no medical basis for the surgery. Some of the main points of the study are:
- Over one-third of women are having elective repeat Cesareans. This is a significant number.
- Delivery just 3 or 4 days before 39 weeks led to increased complications.
- Respiratory problems are more likely with repeat c-sections, as well as other complications, particularly when the surgery is done before 39 weeks or after 40 weeks gestation.
- Parents and Doctors should wait until the 39th week to deliver via repeat elective c-section, and no later than the 40th week.
Subscribe to:
Posts (Atom)